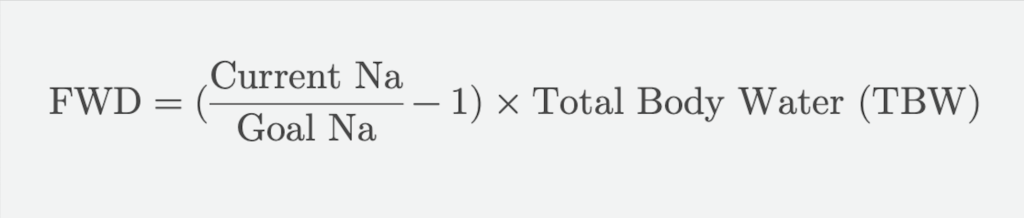TopPodcast.com
Menu
  • Home
  • Top Charts
  • Top Networks
  • Top Apps
  • Top Independents
  • Top Podfluencers
  • Top Picks
    • Top Business Podcasts
    • Top True Crime Podcasts
    • Top Finance Podcasts
    • Top Comedy Podcasts
    • Top Music Podcasts
    • Top Womens Podcasts
    • Top Kids Podcasts
    • Top Sports Podcasts
    • Top News Podcasts
    • Top Tech Podcasts
    • Top Crypto Podcasts
    • Top Entrepreneurial Podcasts
    • Top Fantasy Sports Podcasts
    • Top Political Podcasts
    • Top Science Podcasts
    • Top Self Help Podcasts
    • Top Sports Betting Podcasts
    • Top Stocks Podcasts
  • Podcast News
  • About Us
  • Podcast Advertising
  • Contact
Not in our directory?
Add Show Here
Podcast Equipment
Center

toppodcastlogoOur TOPPODCAST Picks

  • Comedy
  • Crypto
  • Sports
  • News
  • Politics
  • True Crime
  • Business
  • Finance

Follow Us

toppodcastlogoStay Connected

    View Top 200 Chart
    Back to Rankings Page
    Government & Organizations

    Core EM – Emergency Medicine Podcast

    Core EM Emergency Medicine Podcast

    Advertise

    Copyright: © Core EM

    • Apple Podcasts
    • Google Play
    • Spotify

    Latest Episodes:
    Episode 207: Smoke Inhalation Injury Apr 02, 2025
    Show notes

    We discuss the injuries sustained from smoke inhalation.

    Hosts:
    Sarah Fetterolf, MD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Smoke_Inhalation.mp3 Download Leave a Comment Tags: Environmental, Toxicology

    Show Notes

    Table of Contents

    00:37 – Overview of Smoke Inhalation Injury

    00:55 – Three Key Pathophysiologic Processes

    01:41 – Physical Exam Findings to Watch For

    02:12 – Airway Management and Early Intervention

    03:23 – Carbon Monoxide Toxicity

    04:24 – Workup and Initial Treatment of CO Poisoning

    06:14 – Cyanide Toxicity

    07:19 – Treatment Options for Cyanide Poisoning

    09:12 – Take-Home Points and Clinical Pearls

    Physiological Effects of Smoke Inhalation:

    • Thermal Injury:
      • Direct upper airway damage from heated air or steam.
      • Leads to swelling, inflammation, and possible airway obstruction.
    • Chemical Irritation:
      • Causes bronchospasm, mucus plugging, and inflammation in the lower airways.
      • Increases capillary permeability, potentially causing pulmonary edema.
    • Systemic Toxicity:
      • Primarily involves carbon monoxide and cyanide poisoning.

    Clinical Signs and Symptoms:

    • Physical Exam:
      • Facial burns, singed nasal hairs
      • Hoarseness, stridor (upper airway swelling)
      • Carbonaceous sputum (lower airway edema)
    • Systemic Symptoms:
      • Headache, dizziness, nausea
      • Syncope, seizures, altered mental status

    Airway Management Considerations:

    • Not every patient requires immediate intubation.
    • Intubation should be performed early if airway compromise is suspected, as swelling can rapidly progress.
    • Close airway monitoring recommended for all patients.

    Carbon Monoxide Poisoning:

    • Common cause of death post-smoke inhalation (50–75% of fire-related injuries).
    • Hemoglobin affinity 250 times greater for CO than oxygen, impairing tissue oxygenation.
    • Diagnosis:
      • Carboxyhemoglobin level via VBG (ensure proper lab ordering).
      • Pulse oximetry unreliable; falsely high readings.
    • Treatment:
      • Immediate high-flow oxygen administration.
      • Consider hyperbaric oxygen therapy for severe cases to reduce delayed neurocognitive sequelae.

    Cyanide Poisoning:

    • Blocks cytochrome oxidase in electron transport chain, halting aerobic ATP production.
    • Patients present critically ill; notable features include:
      • Elevated lactate levels (>8–10 mmol/L)
      • Arterialization of venous blood
    • Treatment:
      • First-line therapy: hydroxocobalamin (Cyanokit) binds cyanide forming vitamin B12 for renal excretion.
      • Alternative: Cyanide antidote kit (amyl nitrite, sodium nitrite, sodium thiosulfate); induces methemoglobinemia and requires monitoring.
      • Important note: hydroxocobalamin turns blood and urine bright red; draw labs beforehand.

    Key Takeaways:

    • Assess for airway compromise and signs of inhalation injury early.
    • Maintain a high index of suspicion for CO and cyanide poisoning in smoke inhalation victims.
    • Immediate, aggressive oxygen therapy and early antidote administration can significantly impact outcomes.

    Read More

    Episode 206: Acute Back Pain Mar 03, 2025
    Show notes

    We discuss the evaluation of and treatment options for acute back pain.

    Hosts:
    Benjamin Friedman, MD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Acute_Back_Pain.mp3 Download Leave a Comment Tags: Musculoskeletal, Orthopaedics

    Show Notes

    **Please fill out this quick survey to help us develop additional resources for our listeners: Core EM Survey**

    Clinical Evaluation:

    • Primary Goal: Distinguish benign musculoskeletal pain from serious pathology.
    • Red Flags: Look for indicators of spinal infection, spinal bleed, or space-occupying lesions (e.g., tumors, large herniated discs).
    • Assessment: A thorough history and neurological exam (strength testing, gait) is essential.
    • Additional Tools: Use bedside ultrasound for post-void residual assessment in suspected cauda equina syndrome

    Imaging Guidelines:

    • Routine Imaging: Generally not indicated for young, healthy patients without red flags.
    • ACEP Recommendations: Avoid lumbar X-rays in patients under 50 without risk factors, as they do not change management and may increase costs and ED time.
    • Advanced Imaging: Reserve MRI for patients with red flags, neurological deficits, or suspected cauda equina syndrome; CRP may be a part of your calculus when evaluating for infectious causes of back pain

    Treatment Options:

    • Evidence-Based First-Line:
      • NSAIDs offer modest benefit.
      • Skeletal muscle relaxants can be used but require caution due to side effects.
    • Ineffective Therapies:
      • Acetaminophen shows no benefit for back pain.
      • Steroids are not recommended for non-radicular pain, with only limited benefit in sciatica.
      • Topical treatments, lidocaine patches, and opioids are not supported by evidence and may pose additional risks.

    Alternative and Experimental Interventions:

    • Nerve Blocks: Current evidence is limited; more research is needed on trigger point injections and erector spinae plane blocks.
    • Severe Pain Management:
      • A single opioid dose (preferably codeine or oral morphine) may be considered to facilitate discharge when necessary.
      • Use diazepam sparingly for immediate mobilization.
      • Onsite physical therapy in the ED can be beneficial when available.
    • Preventing Chronic Pain:
      • Research Focus: Ongoing studies are evaluating whether duloxetine (Cymbalta) can prevent the transition from acute to chronic back pain.
      • Non-Pharmacologic Measures: Consider spinal mobilization, physical therapy, acupuncture, and cognitive behavioral therapy (CBT) as adjuncts in management.

    Take-Home Points:

    • Most acute back pain is benign, but watch for red flags like IV drug use, anticoagulation, or neurological symptoms (e.g., weakness, bladder dysfunction) that may indicate serious conditions like spinal infections, bleeds, or cord compression.
    • Avoid unnecessary lumbar X-rays in young, healthy patients without red flags—MRI is preferred only for those with risk factors, neurological deficits, or suspected cauda equina syndrome.
    • Use NSAIDs and skeletal muscle relaxants for acute musculoskeletal back pain, as they offer modest benefits. Avoid opioids, acetaminophen, and steroids for non-radicular pain, as they lack evidence.
    • For severe, uncontrolled pain, consider a single opioid dose (e.g., codeine) or diazepam sparingly
    • Encourage patients to engage in non-pharmacologic therapies like yoga, massage, or cognitive behavioral therapy to aid recovery and prevent chronic pain.

    Read More

    Episode 205: Family Presence during Resuscitation Feb 02, 2025
    Show notes

    We discuss the impact of family presence during resuscitations.

    Hosts:
    Ellen Duncan, MD, PhD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Family_Presence_During_Resuscitation.mp3 Download Leave a Comment Tags: Critical Care, Pediatrics

    Show Notes

    Overview

    • Historical Context: The conversation around allowing family members in the room during resuscitation events began gaining attention in 1987. Since then, the practice has been increasingly encouraged.
    • Current Practices in Pediatrics:
      • Family presence during pediatric resuscitations remains inconsistent, with healthcare provider acceptance ranging from 15% to 85%.
      • Many subspecialists and consultants still request that families step out, often due to outdated concerns.
    • Common Concerns & Myths:
      • Interference in resuscitation → Studies show minimal disruption.
      • Legal risks → No increased litigation risk has been demonstrated.
      • Family trauma → Research suggests that presence may help with grieving and reduce PTSD symptoms.

    Evidence from the Literature

    New England Journal of Medicine study on Family Presence During Cardiopulmonary Resuscitation (Jabre et al., 2013):

    • In a randomized controlled trial of 570 relatives, PTSD-related symptoms were significantly higher in family members who were not offered the opportunity to be present during resuscitation.
      • 79% of relatives in the intervention group witnessed CPR compared to 43% in the control group.
      • Family members who did not witness CPR had a higher likelihood of PTSD symptoms (adjusted OR 1.7, p=0.004).
      • Anxiety and depression symptoms were also higher in those who did not witness CPR.
    • Impact on Medical Teams:
      • The study found no evidence that family presence affected resuscitation success rates, medical team stress levels, or led to legal consequences.
      • Health professionals’ concerns over interference were largely unfounded.

    Guideline Support & Barriers to Implementation

    • Professional recommendations from pediatric societies support family presence during resuscitations.
    • Barriers include:
      • Lack of institutional policies ensuring family inclusion.
      • Lack of formal training for providers on how to support families during these critical moments.

    Final Takeaways

    • Encouraging institutional policy changes and training providers is key to implementing family presence during codes.
    • Medical teams should challenge outdated practices and prioritize family-centered care in the emergency department.
    • Family-witnessed resuscitation does not increase stress, legal risk, or compromise medical care—but it can significantly improve bereavement outcomes.

    Read More

    Episode 204: Necrotizing Fasciitis Jan 01, 2025
    Show notes

    We discuss the recognition and treatment of necrotizing fasciitis.

    Hosts:
    Aurnee Rahman, MD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Necrotizing_Fasciitis.mp3 Download Leave a Comment Tags: Critical Care, General Surgery

    Show Notes

    Table of Contents

    0:00 – Introduction

    0:41 – Overview

    1:10 – Types of Necrotizing Fasciitis

    2:21 – Pathophysiology & Risk Factors

    3:16 – Clinical Presentation

    4:06 – Diagnosis

    5:37 – Treatment

    7:09 – Prognosis and Recovery

    7:37 – Take Home points

    Introduction

    • Necrotizing soft tissue infections can be easily missed in routine cases of soft tissue infection.
    • High mortality and morbidity underscore the need for vigilance.

    Definition

    • A rapidly progressive, life-threatening infection of the deep soft tissues.
    • Involves fascia and subcutaneous fat, causing fulminant tissue destruction.
    • High mortality often due to delayed recognition and treatment.

    Types of Necrotizing Fasciitis

    • Type I (Polymicrobial)
      • Involves aerobic and anaerobic organisms (e.g., Bacteroides, Clostridium, Peptostreptococcus).
      • Common in immunocompromised patients or those with comorbidities (e.g., diabetes, peripheral vascular disease).
    • Type II (Monomicrobial)
      • Often caused by Group A Streptococcus (Strep pyogenes) or Staphylococcus aureus.
      • Can occur in otherwise healthy individuals.
      • Vibrio vulnificus (associated with water exposure) is another example.
    • Fournier’s Gangrene (Subset)
      • Specific to perineal, genital, and perianal regions.
      • Common in diabetic patients.
      • Higher mortality, especially in females.

    Pathophysiology

    • Spread Along Fascia
      • Poor blood supply in fascial planes allows infection to advance rapidly.
      • Tissue ischemia worsened by vascular thrombosis → rapid necrosis.
    • High-Risk Patients
      • Diabetes with vascular compromise.
      • Recent surgeries or trauma (introducing bacteria into deep tissue).
      • Immunosuppression (e.g., cirrhosis, malignancy, or immunosuppressive meds).
      • NSAID use may mask symptoms, delaying diagnosis.

    Clinical Presentation

    Early Signs & Symptoms

    • Severe Pain out of proportion to exam findings.
    • Erythema (often with indistinct borders).
    • Fever, Malaise (systemic signs of infection).
    • Rapid progression with possible color changes (red → purple).
    • Bullae Formation (fluid-filled blisters) and skin necrosis/gangrene.
    • Crepitus in polymicrobial cases (gas production in tissue).

    Late-Stage Signs

    • Systemic toxicity: hypotension, multi-organ failure if untreated.

    Diagnosis

    • Clinical Suspicion Is Key
      • Pain out of proportion, rapid progression, systemic signs.
      • The “finger test” (small incision to explore fascial planes).
    • Surgical Consultation
      • Early surgical exploration is often the definitive diagnostic step.
    • Lab Tests
      • LRINEC Score (CRP, WBC, Hemoglobin, Sodium, Creatinine, Glucose) to stratify risk.
      • Not definitive but can guide suspicion.
    • Imaging
      • CT scan may reveal gas in tissues, fascial edema, or muscle involvement.
      • Must not delay surgical intervention if clinical suspicion is high.

    Treatment Principles

    • Immediate & Aggressive Surgical Debridement
      • Often multiple surgical procedures are required as necrosis progresses.
      • Debridement back to healthy tissue margins.
    • Empiric Broad-Spectrum Antibiotics
      • Cover gram-positive (including MRSA), gram-negative, and anaerobes.
      • Examples include:
        • Vancomycin or Linezolid (for MRSA).
        • Piperacillin-tazobactam or Carbapenems (for gram-negative & anaerobes).
        • Clindamycin (to inhibit bacterial toxin production).
      • Adjust based on culture results later.
    • Adjunct Therapies
      • Hyperbaric Oxygen Therapy (if available) for resistant cases.
      • Evidence is mixed; not universally accessible.
    • Supportive Care
      • Intensive monitoring, often in an ICU setting.
      • Fluid resuscitation & vasopressors for septic shock.

    Prognosis & Disposition

    • High Mortality Rate
      • Influenced by infection site, patient’s baseline health, and speed of intervention.
    • Importance of Rapid Intervention
      • Early recognition, aggressive surgery, and antibiotics improve survival.
    • Long-Term Considerations
      • Patients may require extensive rehabilitation.
      • Reconstructive surgery often needed for tissue deficits.
    • Disposition
      • Operative management is mandatory; patients do not go home.
      • Critical care admission is typical for hemodynamic monitoring and support.

    Five Key Take-Home Points

    • High Suspicion Saves Lives: Recognize severe pain out of proportion as a critical red flag.
    • Know Your NF Types & Risk Factors: Type I polymicrobial vs. Type II monomicrobial, plus subsets (Fournier’s).
    • Clinical Diagnosis Above All: LRINEC and imaging help, but timely surgical exploration is paramount.
    • Combined Surgical & Medical Therapy: Early debridement + broad-spectrum antibiotics (including toxin inhibition) is lifesaving.
    • Extended Recovery & Mortality Risks: High mortality if missed or delayed. Expect prolonged rehab and possible multiple surgeries.

    Resources & Further Reading

    • LRINEC Score Calculator
    • EMCrit – Necrotizing Fasciitis

    Read More

    Episode 203: Acetaminophen Toxicity Dec 02, 2024
    Show notes

    We sit down with one of our toxicologists to discuss acetaminophen toxicity.

    Hosts:
    Marlis Gnirke, MD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Acetaminophen_Toxicity.mp3 Download One Comment Tags: Toxicology

    Podcast Video

    Show Notes

    Table of Contents

    0:35 – Hidden acetaminophen toxicity in OTC products

    3:24 – Pharmacokinetics and toxicokinetics

    6:06 – Clinical Course

    9:22 – The antidote – NAC

    11:02 – The Rumack-Matthew Nomogram

    17:36 – Treatment protocols

    22:34 – Monitoring and Lab Work

    23:23 – Considerations when treating pediatric patients

    23:57 – IV APAP overdose, fomepizole

    25:42 – Take Home Points

    Acetaminophen vs. Tylenol:

    • The importance of recognizing that acetaminophen is found in many products beyond Tylenol.
    • Common medications containing acetaminophen, such as Excedrin, Fioricet, Percocet, Dayquil/Nyquil, and others.
    • The risk of unintentional overdose due to combination products.

    Prevalence of Acetaminophen Toxicity:

    • Widespread availability and under-recognition contribute to its prevalence.
    • The potential for unintentional overdose when taking multiple medications containing acetaminophen.

    Pharmacokinetics and Metabolism:

    • Normal metabolism pathways of acetaminophen and the role of glutathione.
    • Formation of the toxic metabolite NAPQI during overdose situations.
    • Saturation of safe metabolic pathways leading to hepatotoxicity.

    Pathophysiology of Liver Injury:

    • How excessive NAPQI leads to hepatocyte death, especially in zone III of the liver.
    • The difference between therapeutic dosing and overdose metabolism.

    Clinical Stages of Acetaminophen Toxicity:

    • Stage 1: Asymptomatic or nonspecific symptoms (first 24 hours).
    • Stage 2: Onset of hepatic injury (24-72 hours), elevated AST/ALT.
    • Stage 3: Maximum hepatotoxicity (72-96 hours), signs of liver failure.
    • Stage 4: Recovery phase, complete hepatic regeneration if survived.

    Antidote – N-Acetylcysteine (NAC):

    • Mechanisms of NAC in replenishing glutathione and detoxifying NAPQI.
    • The importance of early administration, ideally within 8 hours post-ingestion.
    • NAC’s role even in late presenters and in fulminant hepatic failure.

    The Rumack-Matthew Nomogram:

    • How to use the nomogram for acute overdoses to determine the need for NAC.
    • Limitations in chronic overdoses and late presentations.
    • Emphasis on obtaining accurate time of ingestion and acetaminophen levels.

    Treatment Protocols:

    • Standard 21-hour IV NAC protocol and dosing specifics.
    • Managing anaphylactoid reactions associated with IV NAC.
    • Criteria for extending NAC therapy beyond 21 hours.

    Monitoring and Laboratory Work:

    • Importance of trending AST/ALT, INR, creatinine, lactate, and phosphate.
    • Use of the King’s College Criteria for potential liver transplant evaluation.

    Special Considerations:

    • Adjustments in pediatric patients regarding NAC dosing volumes.
    • Awareness of IV acetaminophen overdoses and their management.
    • Emerging discussions on the use of fomepizole in massive overdoses.

    Take-Home Points:

    • Comprehensive Medication History: Always inquire about all medications taken to assess for potential acetaminophen exposure.
    • Early Recognition and Treatment: Due to often silent initial stages, maintain a high index of suspicion and measure acetaminophen levels promptly.
    • Understanding Metabolism and Toxicity: Recognize how overdose alters metabolism, leading to toxic NAPQI accumulation.
    • N-Acetylcysteine Efficacy: NAC is most effective when administered early but remains beneficial even in advanced stages.
    • Proper Use of the Nomogram: Utilize the Rumack-Matthew Nomogram appropriately for acute ingestions and consult toxicology when in doubt.
    • Monitoring and Continuing Care: Be vigilant in monitoring laboratory values and prepared to extend NAC therapy as needed.
    • Consultation and Resources: Engage with poison control centers and utilize available resources for complex cases.

    Resources Mentioned

    Rumack-Matthew Nomogram

    Rumack-Matthew Nomogram, credit: MDCalc

    King’s College Criteria

    • King’s College Criteria for Acetaminophen Toxicity
    • Use this tool to assess the need for liver transplant evaluation in cases of acetaminophen-induced hepatic failure. Includes criteria for pH, INR, creatinine, and more.

    Poison Control Center (available 24/7 for consultation): 1-800-222-1222

    References

    • Goldfrank’s Toxicologic Emergencies, 9th Edition was consulted for information on the pharmacokinetics and clinical presentation of acetaminophen toxicity.
    • For more details, see: Nelson, L. S., Howland, M. A., Lewin, N. A., Smith, S. W., Goldfrank, L. R., & Hoffman, R. S. (Eds.). (2011). Goldfrank’s toxicologic emergencies (9th ed.). McGraw-Hill Education.

    Read More

    Episode 202: Sexually Transmitted Infections 2.0 Nov 01, 2024
    Show notes

    We review Sexually Transmitted Infections and pertinent updates in diagnosis and management.

    Hosts:
    Avir Mitra, MD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Sexually_Transmitted_Infections_2_0.mp3 Download Leave a Comment Tags: gynecology, Infectious Diseases, Urology

    Show Notes

    Table of Contents

    (1:49) Chlamydia

    (3:31) Gonorrhea

    (4:50) PID

    (6:14) Syphilis

    (8:08) Neurosyphilis

    (9:13) Tertiary Syphilis

    (10:06) Trichomoniasis

    (11:13) Herpes

    (12:49) HIV

    (14:10) PEP

    (15:13) Mycoplasma Genitalium

    (18:00) Take Home Points

    Chlamydia:

    • Prevalence:
        • Most common STI.
        • High percentage of asymptomatic cases (40% to 96%).
    • Presentation:
        • Urethritis, cervicitis, pelvic inflammatory disease (PID), prostatitis, proctitis, pharyngitis, arthritis.
        • Importance of considering extra-genital sites (oral and rectal infections).
    • Testing:
        • Gold Standard: Nucleic Acid Amplification Test (NAAT) via PCR.
    • Sampling Sites:
          • Endocervical or urethral swabs preferred over urine samples due to higher sensitivity.
          • Triple-site testing (genital, rectal, pharyngeal) recommended for comprehensive detection.
    • Treatment Updates:
        • Previous Regimen: Azithromycin 1 g orally in a single dose.
        • Current First-Line Treatment: Doxycycline 100 mg orally twice daily for 7 days.
    • Alternatives:
        • Azithromycin remains an option for patients unlikely to adhere to a 7-day regimen or for pregnant patients.
      • Note: PID treatment differs and will be discussed separately.

    Gonorrhea:

    • Presentation:
        • Similar to chlamydia; can be asymptomatic.
        • Symptoms include urethritis, cervicitis, PID, prostatitis, proctitis, pharyngitis.
    • Testing:
        • Gold Standard: NAAT.
    • Sampling Sites:
          • Endocervical swabs are more sensitive than urine samples.
          • Triple-site testing is crucial to avoid missing infections.
    • Treatment Updates:
        • Previous Regimen: Ceftriaxone 250 mg IM plus azithromycin 1 g orally.
        • Current Recommendation: Ceftriaxone 500 mg IM single dose.
          • Adjusted due to rising azithromycin resistance and updated pharmacokinetic data.
    • Co-Infection Considerations:
      • High rates of chlamydia and gonorrhea co-infection (20% to 40%).
      • CDC recommends empiric treatment for chlamydia when treating gonorrhea to prevent complications like PID and infertility.

    Pelvic Inflammatory Disease (PID):

    • Etiology:
        • Not solely caused by chlamydia and gonorrhea; about 50% of cases involve other pathogens like bacterial vaginosis (BV) organisms and anaerobes.
    • Treatment Changes:
    • Expanded Coverage Regimen:
        • Ceftriaxone 500 mg IM once.
        • Doxycycline 100 mg orally twice daily for 14 days.
        • Metronidazole 500 mg orally twice daily for 14 days.
      • Inclusion of metronidazole addresses anaerobic bacteria contributing to PID.

    Syphilis:

    • Stages and Presentation:
    • Primary Syphilis:
        • Painless chancre on genitals.
        • Treatment: Penicillin G 2.4 million units IM single dose.
    • Secondary Syphilis:
        • Rash (often diffuse), mucocutaneous lesions, nonspecific joint pain.
        • Treatment: Same as primary syphilis.
    • Latent Syphilis:
        • Asymptomatic phase; divided into early (<1 year) and late (>1 year).
    • Treatment for Late Latent:
      • Penicillin G 2.4 million units IM once weekly for 3 weeks.
      • Recommended when the timing of infection is unclear.

    Neurosyphilis:

    • Can occur at any stage.
    • Symptoms include visual changes, severe headaches, neurological deficits.
    • Diagnosis: Requires lumbar puncture (LP) for confirmation.
    • Treatment: Admission for intravenous penicillin G.

    Tertiary Syphilis:

    • Rare, advanced stage with severe manifestations (e.g., gummas, cardiovascular complications, neurological signs).
    • Treatment: Extended penicillin therapy similar to late latent syphilis.

    Trichomoniasis:

    • Presentation:
        • Often asymptomatic.
        • In women: Vaginal discharge.
        • In men: Urethritis.
    • Testing:
        • Shift from wet mount microscopy to NAAT for improved detection.
        • Swab samples preferred over urine for higher sensitivity.
    • Treatment Updates:
        • Previous Regimen: Metronidazole 2 g orally in a single dose.
    • Current Recommendations:
        • Women: Metronidazole 500 mg orally twice daily for 7 days.
        • Men: Single 2 g dose remains acceptable.

    Herpes Simplex Virus (HSV):

    • Types and Transmission:
        • HSV-1 and HSV-2: Both can cause oral and genital infections.
        • Increasing crossover between oral and genital sites.
    • Testing:
        • Serum IgG testing not useful for acute diagnosis due to widespread prior exposure.
        • Preferred Method: PCR testing from lesion swabs.
      • Clinical Tip: If the lesion is characteristic, clinicians may start treatment without waiting for test results.
    • Treatment:
        • Preferred Medication: Valacyclovir (Valtrex) for ease of dosing.
    • Dosage:
        • Initial episode: 1 g orally twice daily for 7 to 10 days.
        • Recurrence: 1 g daily for 5 days.
      • Alternative: Acyclovir for cost considerations.

    Human Immunodeficiency Virus (HIV):

    • Testing Limitations:
    • Window Periods:
          • Fourth-generation tests have a window period of 2 to 4 weeks.
          • Negative results during this period may not rule out recent infection.
    • Acute HIV Infection:
        • Presents with flu-like symptoms: malaise, joint pains, fatigue.
    • Diagnosis Challenges:
        • Standard HIV tests may be negative during the window period.
    • Options:
          • Empiric treatment with follow-up testing.
          • Order an HIV viral load test (more sensitive but expensive and delayed results).
    • Post-Exposure Prophylaxis (PEP):
        • Timing: Initiate ideally within 72 hours of potential exposure.
        • Duration: 28-day regimen.
    • Pre-Treatment Testing:
      • Baseline HIV test to rule out existing infection.
      • Renal and hepatic function tests to monitor for medication side effects.
    • Follow-Up: Reassess renal/hepatic function in 2 weeks.

    Mycoplasma genitalium:

    • Recognition:
        • Newly recognized STI by the CDC in 2021.
        • Causes cervicitis and urethritis.
        • Possible associations with PID and proctitis, but not definitively established.
    • Testing:
    • When to Test:
          • Only in patients with persistent symptoms after standard STI testing and treatment.
          • Not recommended for initial screening.
        • Method: NAAT.
    • Treatment:
        • Step 1: Doxycycline 100 mg orally twice daily for 7 days.
        • Step 2: Moxifloxacin 400 mg orally once daily for 7 days.
        • Addresses antibiotic resistance concerns and ensures comprehensive treatment.
    • General Management and Patient Counseling:
    • Partner Notification:
          • Encourage patients to inform sexual partners for testing and treatment.
    • Medication Adherence:
          • Emphasize the importance of completing the full course of prescribed medications.
    • Prevention Measures:
          • Discuss the use of barrier protection (e.g., condoms) to prevent transmission and reinfection.
    • Follow-Up Care:
        • Advise patients to return if symptoms persist, indicating possible infections like Mycoplasma genitalium.

    Key Take-Home Points:

    • Chlamydia Treatment Update:
        • Doxycycline 100 mg orally twice daily for 7 days is now first-line treatment for cervical infections.
        • For epididymitis, extend doxycycline to 10 days.
    • Gonorrhea Treatment Update:
        • Treat with a single 500 mg IM dose of ceftriaxone.
    • PID Management Update:
        • Expanded antimicrobial coverage includes:
          • Ceftriaxone 500 mg IM once.
          • Doxycycline 100 mg orally twice daily for 14 days.
          • Metronidazole 500 mg orally twice daily for 14 days.
    • Mycoplasma genitalium Recognition:
        • Test in patients with persistent symptoms after standard treatment.
        • Treat with doxycycline followed by moxifloxacin.
    • HIV Testing and PEP:
      • Be aware of HIV test window periods; negative results may not rule out recent infection.
      • Consider HIV viral load testing if acute infection is suspected.
      • Initiate PEP within 72 hours for a 28-day course, ensuring clear discharge planning and patient support.

    Read More

    Episode 201: Migraines Oct 01, 2024
    Show notes

    We discuss migraines with one of the authorities in the field.

    Hosts:
    Benjamin Friedman, MD of Montefiore
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Migraines.mp3 Download Leave a Comment Tags: Neurology

    Show Notes

    Initial Approach to Diagnosing Migraines:

    • Differentiating between primary headaches (migraine, tension-type, cluster) and secondary causes (e.g., subarachnoid hemorrhage).
    • The importance of patient history and reevaluation after initial treatment.
    • Recognizing the unique presentation of cluster headaches and their management implications.

    Effective Acute Migraine Treatments:

    • First-line treatments including anti-dopaminergic medications like metoclopramide (Reglan) and prochlorperazine (Compazine), and parenteral NSAIDs like ketorolac (Toradol).
    • The limited role of triptans in the ED due to side effects and less efficacy compared to anti-dopaminergics.
    • The use of nerve blocks (greater occipital nerve block and sphenopalatine ganglion block) as effective treatments without systemic side effects.

    Treatments to Avoid or Use with Caution:

    • Diphenhydramine (Benadryl): Studies show it does not prevent akathisia from anti-dopaminergics nor improve migraine outcomes.
    • IV Fluids: Routine use is not supported unless the patient shows signs of dehydration.
    • Magnesium: Conflicting evidence with some studies showing no benefit or even harm.

    Managing Refractory Migraines:

    • Second-line treatments including additional doses of metoclopramide combined with NSAIDs or dihydroergotamine (DHE).
    • Considering opioids as a last resort when other treatments fail.
    • The potential use of newer medications like lasmiditan and CGRP antagonists.

    Preventing Recurrence of Migraines:

    • Administering a single dose of dexamethasone (4 mg IV) to reduce the risk of headache recurrence after discharge.
    • Prescribing NSAIDs or triptans upon discharge for outpatient management.
    • Recognizing and addressing chronic migraine, and initiating preventive therapies like propranolol when appropriate.

    Key Takeaways

    • Differentiate Primary from Secondary Headaches and Reassess After Treatment:
      • Use patient history and reevaluation post-treatment to distinguish migraines from more serious conditions, reducing unnecessary imaging and procedures.
    • First-Line Treatments Are Effective:
      • Anti-dopaminergic medications and NSAIDs are the mainstay of acute migraine treatment in the ED.
      • Reserve opioids for cases unresponsive to multiple lines of treatment.
    • Avoid Unnecessary Interventions:
      • Diphenhydramine and routine IV fluids do not have proven benefits and can be excluded to streamline care.
    • Utilize Nerve Blocks for Refractory Cases:
      • Greater occipital nerve blocks and sphenopalatine ganglion blocks are effective alternatives for patients not responding to medication.
    • Prevent Recurrence with Dexamethasone and Outpatient Planning:
      • A single IV dose of dexamethasone can help prevent recurrence.
      • Provide prescriptions and consider preventive therapies to reduce future ED visits.

    Read More

    Episode 200: Immune Checkpoint Inhibitors Sep 02, 2024
    Show notes

    We discuss a new class of medications, Immune Checkpoint Inhibitors, and their side effects.

    Hosts:
    Avir Mitra, MD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Immune_Checkpoint_Inhibitors.mp3 Download Leave a Comment Tags: Oncology

    Show Notes

    Overview of Immune Checkpoint Inhibitors (ICIs)

    • ICIs are a relatively new class of oncologic drugs that have revolutionized cancer treatment.
    • Unlike chemotherapy, ICIs help the immune system develop memory against cancer cells and adapt as the cancer mutates.
    • Since their release in 2011, ICIs have expanded to 83 indications for 17 different cancers, with approximately 230,000 patients using them.

    Mechanism of Action

    • Cancer cells can evade the immune system by binding to T cell receptors that downregulate the immune response.
    • ICIs work by blocking these receptors or ligands, preventing the downregulation and allowing T cells to proliferate and attack cancer cells.
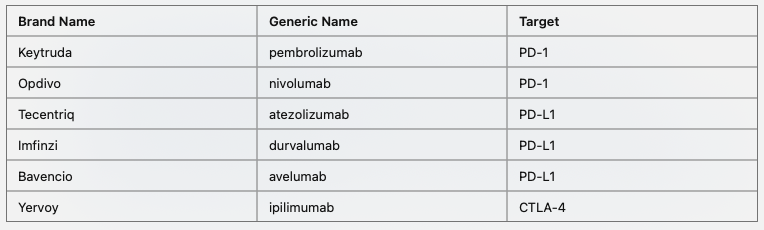
    • Common ICIs

    Risks and Toxicities of ICIs

    • ICIs can lead to autoimmune attacks on healthy cells due to immune system upregulation.
    • Immune-related adverse effects (irAEs) include colitis, pneumonitis, dermatitis, hepatitis, and endocrine issues (e.g., hypothyroid, hypocortisolemia, hypophysitis).
    • These toxicities can present as infections, making diagnosis challenging in the emergency room.

    Management of ICI Toxicities in the ER

    • Diagnosis: Look for signs that mimic infections (e.g., cough and fever in pneumonitis).
    • Diagnostic Imaging in pneumonitis: If CXR is normal but suspicion is high, consider CT scans to differentiate conditions like pneumonitis from other issues such as malignancy-associated pleural effusion or acute pulmonary embolism.
    • Treatment: The primary treatment for irAEs is steroids (e.g., prednisone 1 mg/kg). Start steroids early and hold the ICI to manage symptoms effectively and increase the likelihood of resuming ICI therapy later.
    • Consider using antibiotics in combination with steroids if there is uncertainty about whether symptoms are due to infection or ICI toxicity.
    • Coordinate care with the patient’s oncologist if possible

    Disposition Decisions

    • Patient disposition (admit vs. discharge) should depend on clinical presentation and severity.
    • Coordination with oncology is crucial; they are often comfortable with starting steroids even if there is a potential infection.
    • Patients can be discharged if symptoms are mild, but sicker patients with more complex presentations may require admission.

    Take-Home Points

    • ICIs are a new class of cancer drugs that effectively target cancer cells but come with unique immune-related toxicities.
    • Diagnosing irAEs can be challenging due to symptom overlap with infections.
    • The cornerstone of treatment is early administration of steroids and temporarily holding the ICI.
    • Close collaboration with oncology teams is essential for optimal patient management.

    Read More

    Episode 199: Ataxia in Children Aug 01, 2024
    Show notes

    We discuss a case of ataxia in children and how to approach the evaluation of these pts.

    Hosts:
    Ellen Duncan, MD, PhD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Ataxia_in_Children.mp3 Download Leave a Comment Tags: Neurology, Pediatrics

    Show Notes

    Introduction

    • The episode focuses on ataxia in children, which can range from self-limiting to life-threatening conditions.
    • Pediatric emergency medicine specialist shares insights on the topic.

    The Case

    • An 18-month-old boy presented with ataxia, unable to keep his head up, sit, or stand, and began vomiting.
    • Previously healthy except for recurrent otitis media and viral-induced wheezing.
    • The decision to take the child to the emergency department (ED) was based on acute symptoms.

    Differential Diagnosis

    • Common causes include acute cerebellar ataxia, drug ingestion, Guillain-Barre syndrome, and basilar migraine.
    • Less common causes include cerebellitis, encephalitis, brain tumors, and labyrinthitis.

    Importance of History and Physical Examination

    • A detailed history and physical exam are essential in diagnosing ataxia.
    • Key factors include time course, recent infections, signs of increased intracranial pressure, and toxic exposures.
    • Look for signs such as bradycardia, hypertension, vomiting, and overall appearance.

    Diagnostic Workup

    • Initial tests include point-of-care glucose and neuroimaging for concerns about trauma or increased intracranial pressure.
    • MRI is preferred for posterior fossa abnormalities, but non-contrast head CT is commonly used due to accessibility.
    • Lumbar puncture may be needed if meningismus is present.

    Treatment Approach

    • Treatment depends on the underlying cause:
      • Acute cerebellar ataxia is self-limiting and typically resolves with time.
      • Antibiotics are required for meningitis or encephalitis.
      • Steroids may be useful for cerebellitis and acute disseminated encephalomyelitis (ADEM).
      • Specialist consultations are necessary for severe diagnoses like intracranial masses.

    Outcome of the Case Study

    • The child had a normal fast T2 MRI and improved during the ED stay.
    • Diagnosed with a combination of cerebellar ataxia and labyrinthitis.
    • Received myringotomy tubes and experienced no further neurologic changes or otitis media episodes.

    Take-Home Points

    1. Diverse Etiologies: Ataxia in children can have various causes that range from self-limiting to life-threatening
    2. Comprehensive Assessment: History and physical exams guide diagnosis and workup direction, focusing on symptom time course, infections, and toxic exposures.
    3. Physical Examination Clues: Vital signs and appearance offer clues; increased ICP may present with bradycardia, hypertension, and vomiting.
    4. Diagnostic Imaging: Point-of-care glucose testing and neuroimaging are key; MRI is preferred for posterior fossa abnormalities.
    5. Tailored Treatment: Treatment varies by cause; acute cerebellar ataxia typically resolves over time without specific intervention.

    Read More

    Episode 198: Hypernatremia Jul 01, 2024
    Show notes

    We discuss the approach to diagnosing and managing hypernatremia in the emergency department.

    Hosts:
    Abigail Olinde, MD
    Brian Gilberti, MD

    https://media.blubrry.com/coreem/content.blubrry.com/coreem/Hypernatremia.mp3 Download One Comment Tags: Electorlye

    Show Notes

    Episode Overview:

    • Introduction to Hypernatremia
    • Definition and basic concepts
    • Clinical presentation and risk factors
    • Diagnosis and management strategies
    • Special considerations and potential complications

    Definition and Pathophysiology:

    • Hypernatremia is defined as a serum sodium level over 145 mEq/L.
    • It can be acute or chronic, with chronic cases being more common.
    • Symptoms range from nausea and vomiting to altered mental status and coma.

    Causes of Hypernatremia based on urine studies:

    • Urine Osmolality > 700 mosmol/kg
      • Causes:
        • Extrarenal Water Losses: Dehydration due to sweating, fever, or respiratory losses
        • Unreplaced GI Losses: Vomiting, diarrhea
        • Unreplaced Insensible Losses: Burns, extensive skin diseases
        • Renal Water Losses with Intact AVP Response:
        • Diuretic phase of acute kidney injury
        • Recovery phase of acute tubular necrosis
        • Postobstructive diuresis
    • Urine Osmolality 300-600 mosmol/kg
      • Causes:
        • Osmotic Diuresis: High glucose (diabetes mellitus), mannitol, high urea
        • Partial AVP Deficiency: Incomplete central diabetes insipidus
        • Partial AVP Resistance: Nephrogenic diabetes insipidus
    • Urine Osmolality < 300 mosmol/kg
      • Causes:
        • Complete AVP Deficiency: Central diabetes insipidus
        • Complete AVP Resistance: Nephrogenic diabetes insipidus
    • Urine Sodium < 25 mEq/L
      • Causes:
        • Extrarenal Water Losses with Volume Depletion: Vomiting, diarrhea, burns
        • Unreplaced Insensible Losses: Sweating, fever, respiratory losses
    • Urine Sodium > 100 mEq/L
      • Causes:
        • Sodium Overload: Ingestion of salt tablets, hypertonic saline administration
        • Salt Poisoning: Deliberate or accidental ingestion of large amounts of salt
    • Mixed or Variable Urine Sodium
      • Causes:
        • Diuretic Use: Loop diuretics, thiazides
        • Adrenal Insufficiency: Mineralocorticoid deficiency
        • Osmotic Diuresis with Renal Water Losses: High glucose, mannitol

    Risk Factors:

    • Patients with impaired thirst response or those unable to access water (e.g., altered or ventilated patients) are at higher risk.
    • Important to consider underlying conditions affecting thirst mechanisms.

    Diagnosis:

    • Initial assessment includes history, physical examination, and laboratory tests.
    • Key tests: urine osmolality and urine sodium levels.
    • Lab errors should be considered if the clinical picture does not match the lab results.

    Management Strategies:

    • Calculate the Free Water Deficit (FWD) to guide treatment.

    • Administration routes include oral, NGT, G-tube, or IV with D5W for larger deficits.
    • Safe correction rate is 10-12 mEq/L per day or 0.5 mEq/L per hour to avoid cerebral edema.
    • Address hypovolemia with isotonic fluids before correcting sodium.

    Monitoring and Follow-Up:

    • Monitor sodium levels every 4-6 hours.
    • Assess urine output and adjust free water administration as needed.
    • Admission to ICU for symptomatic patients or those with severe hypernatremia (sodium >160 mEq/L).
    • Decision to discharge vs admit is a complicated one that factors in symptoms, etiology, degree of hypernatremia, patient preference, access to follow up, etc.

    Take Home Points:

    • Hypernatremia is a serum sodium level over 145 mEq/L, with symptoms ranging from nausea to coma.
    • It is primarily caused by water loss exceeding intake due to various factors like sweating, vomiting, diarrhea, and renal issues.
    • Correcting hypernatremia too quickly can lead to cerebral edema, so a safe correction rate is essential.
    • Initial treatment involves calculating the Free Water Deficit and selecting the appropriate administration route.
    • Monitor sodium levels frequently and decide on admission or discharge based on symptoms, sodium levels, and patient’s ability to follow up.

    Read More

    Previous 1 2 3 4 5 24 Next

    Related Podcasts

    The Joe Rogan Experience

    1

    The Joe Rogan Experience Comedy
    More Perfect

    2

    More Perfect Government
    Casefile True Crime

    3

    Casefile True Crime Games & Hobbies
    Reply All

    4

    Reply All Games & Hobbies
    You Must Remember This

    5

    You Must Remember This Games & Hobbies
    Real Time with Bill Maher

    6

    Real Time with Bill Maher Games & Hobbies
    footer-logo

    Contact Us

    Toll Free: 844-670-7747

    Links

    • Home
    • Top Charts
    • Networks
    • Apps
    • Independents Podcasts
    • Podcast Advertising
    • Podcast News
    • Contact Us
    • About Us
    • Analytics & Insights

    Stay Connected

      Privacy, Terms of Use & Our Code of Ethics Protecting Content Creators Copyrights